


What is DPC data? Some Explanations about techniques for best usage, analysis methods, and differences with receipt data
Do you know “DPC data”? Even if you know the word somehow, there are few people who understand the meaning and where it applies.
In this article, we would like to provide:
- An explanation of “DPC” and terms related to DPC
- A description of DPC data content & meaning
- DPC data analysis methods and utilization techniques
Our explanation is in plain language, avoiding technical jargon and complex representations. Thanks to our illustrations and diagrams, we hope that you will get the full meaning of it.
What is DPC?
First of all, we should explain what the acronym stands for and what is the meaning of the word “DPC”. DPC is an abbreviation for “Diagnosis Procedure Combination”. It refers to the combination of diagnosis and procedure inside the hospitals.
For example, we classify patients according to their “diagnosis” and “treatment content,” with the image of creating a combination classification where the vertical axis is the diagnosis and the horizontal axis is the treatment content.
This DPC is a relatively new concept and is based on the “DPC system”, what refers to DPC/PDPS (Diagnosis Procedure Combination/Per-Diem Payment System) and was introduced in 2003 in Japan. It is a system designed to comprehensively evaluate inpatient medical care for acute-phase patients (those requiring immediate medical treatment) primarily at large hospitals that meet specific criteria.
“Comprehensive” means that the system adopts a flat-rate remuneration model instead of the traditional fee-for-service system (where medical fees accrue based strictly on the quantity of services performed).
In principle, medical care should provide patients with efficient, affordable, and high-quality treatment. Under the fee-for-service payment system, however, performing more tests and procedures directly increased hospital revenue, creating financial incentives that could sometimes compromise a truly “patient-first” care approach.
By adopting the DPC flat-rate payment model, hospital management is encouraged to prioritize both cost-performance and healthcare quality simultaneously. As a result, medical institutions can realize “patient-first” healthcare aimed at:
- Early discharge through efficient treatment
- Provision of evidence-based standard medical care
- Reduction of unnecessary tests and medications
What is DPC data
Standardized clinical procedure data for patients treated at DPC claim hospitals or hospitals that have submitted notification for data submission is called DPC data. Hospitals generating DPC data are predominantly medical institutions treating acute illnesses, typically characterized by relatively large bed capacities.
What is the DPC Code?
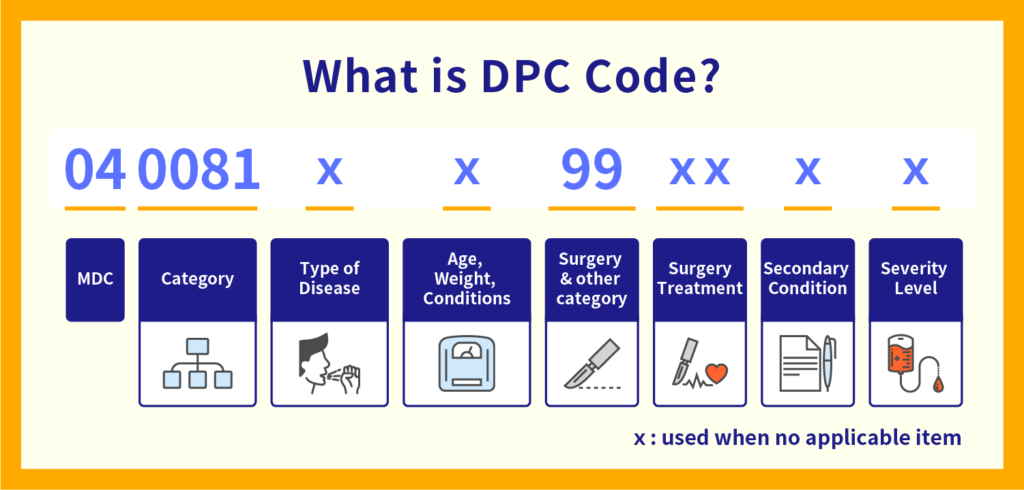
The DPC code is a 14-digit number used to determine the daily hospitalization fee. One code is assigned per hospital admission with no duplication. For example, if a patient is hospitalized with two conditions, such as falling and breaking an arm while admitted for pneumonia, the code representing the condition that consumed the most medical resources during that hospitalization will be selected. The structure of the 14-digit DPC code provides the following information.
The first 6 digits indicate “the disease that invested the most medical resources during hospitalization,” and is called the “basic DPC”.
A code is determined for each disease. For example, aspiration pneumonia will be encoded as “040081”. The first two digits of these six digits are called MDC (major disease category), which simply indicates the broad medical category. In the case of aspiration pneumonia, it becomes a respiratory disease and is written as 04.
The 7th digit represents the classification of pathology, etc., but since 2006, this classification has not been revised.
The 8th digit may be entered when clinical status affecting treatment, such as age, birth weight, or Japan Coma Scale (JCS) consciousness score, applies.
The 9th and 10th digits are called “surgical subclassifications” and are assigned according to surgical procedures performed for each disease based on the basic DPC. If surgery is not required (e.g., for aspiration pneumonia), it is coded as 99.
The 11th / 12th digits may be when specific non-surgical treatments (such as radiation therapy or chemotherapy) are performed.
The 13th / 14th digits are assigned according to the severity of other illnesses that occurred during hospitalization.
What is the content of DPC Data?
In this part, we would like to describe the concrete meaning of the data. DPC Data could be categorized as shown in the table below:
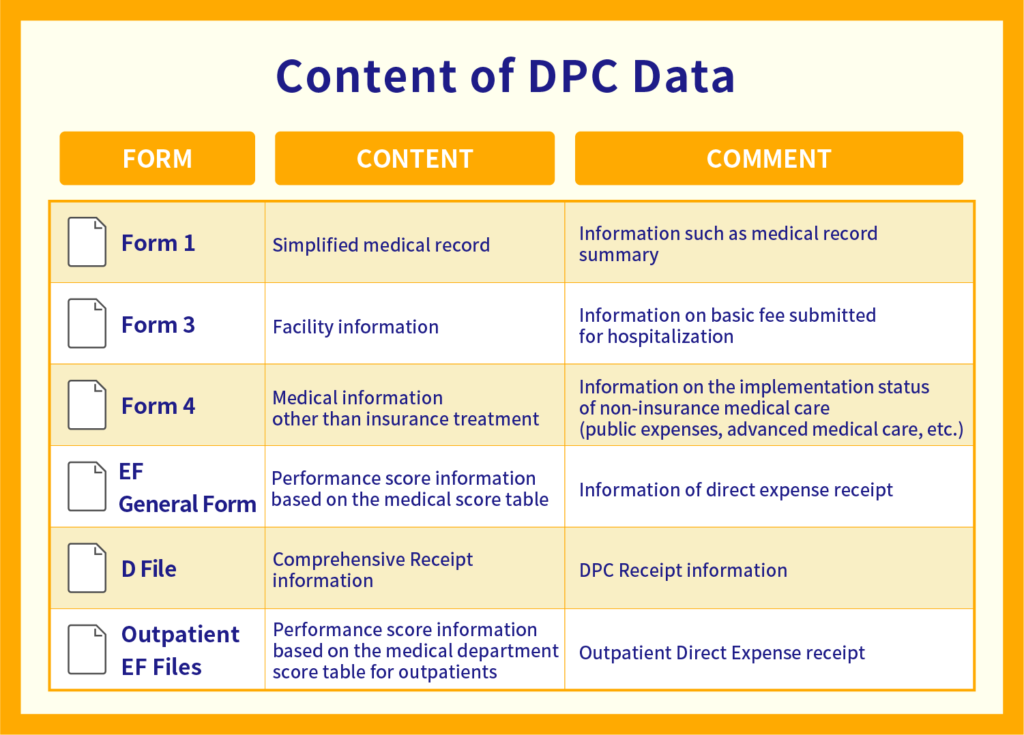
DPC data is organized and composed of several files, as outlined below:
The Form 1 file is the patient’s individual information, such as the “discharge summary” where the doctor summarizes the patient’s hospitalization information at the time of discharge, such as the state of consciousness at the time of admission, date of birth, discharge destination, name of disease, etc.
The Form 3 file provides information on facility infrastructure and staffing, such as reported basic hospitalization fee categories and bed capacity.
The Form 4 file covers payments made outside standard medical insurance coverage.
The EF file summarizes pharmaceutical information for both inpatient and outpatient care, including the types and quantities of drugs used during treatment, as well as administration periods.
The D file summarizes fee points (charges) incurred for inpatient care, including diagnostic tests, medications, and injections.
Main Features of the DPC database
When these DPC data files are compiled, they form the DPC Database. Its greatest feature is the abundance and richness of patient clinical data. The main strength of DPC data lies in its capacity to track comprehensive parameters, including a patient’s clinical state from admission to discharge, medical treatments, pharmaceuticals administered, and fee points.
About DPC public data
DPC public data consists of statistical information compiled annually by the Ministry of Health, Labour and Welfare (MHLW) by aggregating DPC data from across Japan.
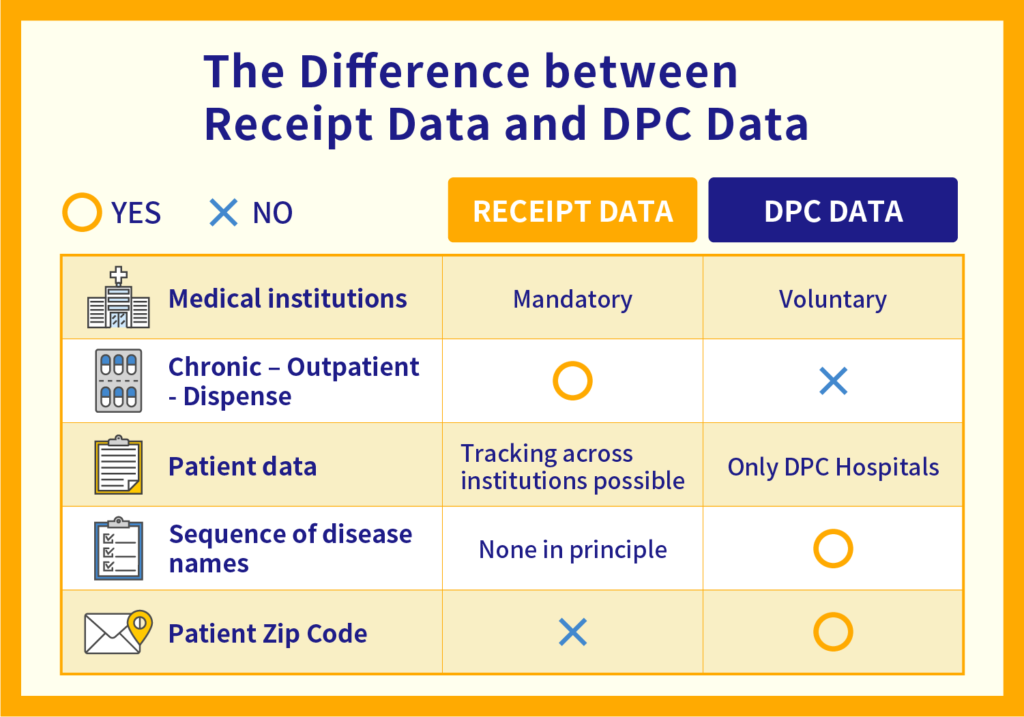
While this information comprehensively covers inpatient DPC data nationwide at the facility level, detailed clinical practice information for individual inpatient or outpatient care cannot be reviewed. Furthermore, because these are annual cross-sectional statistical results, caution is required when conducting time-series longitudinal analysis.
On the other hand, because DPC public data represents a large-scale nationwide census covering healthcare institutions across Japan, it offers significant advantages: metrics such as average length of stay (ALOS) comparisons between hospitals and inpatient counts by MDC can be analyzed and compared at a very granular facility level.
DPC data analysis methods and utilization techniques
Finally, let us discuss how to analyze and utilize DPC data.
From a hospital management standpoint, comparing annual DPC data helps improve administrative efficiency and leads directly to enhanced clinical quality. Hospital leadership can recognize that aiming for high-quality care, without performing unnecessary tests, naturally translates into revenue optimization and sustainable management.
For policymakers and system designers, the database provides a comprehensive bird’s-eye view of which hospitals deliver what level of quality care and their corresponding earnings. This dataset is highly valuable for optimizing regional and national healthcare delivery structures.
Although its coverage target is specific, DPC data offers much deeper clinical content than standard medical claims data. Utilizing it effectively holds significant potential for advancing treatment outcomes, as well as driving pharmaceutical and medical device R&D.
For Those Considering the Utilization of Medical Big Data
At Medical Data Vision (MDV), we offer tools to dramatically increase efficiency in clinical database analysis, as well as customized survey and analysis services for specific medical datasets.
From the Form 1 file (admission/discharge summary data) within the DPC data discussed in this article, we maintain data parameters capable of evaluating disease severity, including patient height and weight, cancer staging, cardiac function, and liver function classifications. Our datasets are widely utilized by pharmaceutical companies, medical device manufacturers, and healthcare enterprises.
For detailed service information or consultation regarding medical big data, please feel free to contact us below:

For More Information, Please Contact Us Here
About Japanese Healthcare System

What you need to know about the healthcare system in Japan before using the data.
SERVICE

In addition to various web tools that allow you to easily conduct surveys via a browser using our medical database, we offer data provision services categorized into four types to meet your needs and challenges: "Analysis reports" "Datasets," "All Therapeutic Areas Data Provision Service," and "Specific Therapeutic Areas Data Provision Service.


© Medical Data Vision Co., Ltd. All Rights Reserved.